The Prescription You Never Finished: Understanding Why Patients Abandon Medications—and How to Build a Regimen That Actually Lasts
Somewhere in the United States right now, a person with hypertension is skipping their morning blood pressure pill. A diabetic patient has let their metformin prescription lapse. Someone managing depression has quietly stopped their antidepressant because the side effects felt worse than the condition itself. None of these individuals are being reckless. Each has a reason—often a very understandable one.
Medication non-adherence affects approximately 50 percent of patients with chronic conditions in the United States. It contributes to roughly 125,000 preventable deaths each year and accounts for an estimated 10 percent of all hospitalizations. Despite these numbers, the conversation between patients and prescribers about adherence remains remarkably shallow in most clinical encounters.
At TabOrderRx, we work with patients navigating complex medication regimens every day. This article is an attempt to address the adherence problem honestly—not by assigning blame, but by examining the real forces that cause patients to abandon prescriptions and identifying practical solutions that reflect how people actually live.
Why Patients Stop: Beyond Forgetfulness
The most common explanation offered for non-adherence is forgetfulness, and it is genuinely a factor. But reducing the problem to absent-mindedness obscures a more complicated reality.
Side effects that were never adequately explained. When a patient begins a new medication and experiences fatigue, nausea, sexual dysfunction, or cognitive fog, they frequently have no framework for evaluating whether what they are feeling is normal, temporary, dangerous, or worth enduring. Without clear guidance, many patients make the rational decision to stop.
Cost. A 2023 survey by the Kaiser Family Foundation found that approximately 29 percent of American adults reported not taking medications as prescribed due to cost. Skipping doses, splitting pills, and simply not filling prescriptions are widespread cost-management strategies that patients rarely disclose to their physicians.
Asymptomatic conditions. Hypertension, high cholesterol, and elevated blood sugar often produce no perceptible symptoms. When a medication makes a patient feel worse than the underlying condition did, the calculus of adherence shifts dramatically. It is cognitively difficult to take a pill that makes you feel bad in order to prevent a heart attack that has not happened yet.
Therapeutic nihilism. Some patients, particularly those managing long-term conditions without obvious improvement, lose faith that their medication is working. Without measurable feedback—the kind a blood pressure cuff or A1C test can provide—adherence becomes an act of trust that erodes over time.
Regimen complexity. Research published in the Annals of Internal Medicine has consistently shown that adherence rates decline as the number of daily doses increases. A patient taking one pill once daily will adhere at significantly higher rates than a patient managing four medications across multiple daily doses.
Stigma and identity. For many patients, especially those managing mental health conditions or substance use disorders, the act of taking medication carries psychological weight. Some patients associate daily pills with a loss of autonomy or a permanent label they are unwilling to accept.
The Consequences That Accumulate Silently
Non-adherence rarely produces an immediate, dramatic consequence. Instead, it operates quietly. Blood pressure creeps upward over weeks. Blood glucose climbs gradually. Depression symptoms return slowly enough that the patient attributes the change to life circumstances rather than the absence of medication.
By the time the consequences become clinically visible—a stroke, a hospitalization, a mental health crisis—the connection to adherence is often missed or minimized. The patient is treated for the acute event without addressing the underlying pattern that produced it.
This is part of what makes non-adherence so difficult to address: the feedback loop between stopping a medication and experiencing its consequences is often too long and too diffuse to feel causal.
Evidence-Based Strategies That Actually Work
The research on medication adherence has identified a number of interventions with meaningful efficacy. They vary considerably in complexity and cost.
Simplify the regimen whenever possible. If you are managing multiple medications, ask your prescriber or pharmacist whether any can be consolidated into combination formulations, shifted to once-daily dosing, or eliminated. This is a legitimate clinical conversation, and pharmacists are particularly well-positioned to facilitate it.
Synchronize your refills. Prescription synchronization programs allow all of your maintenance medications to be filled on the same day each month. This reduces the number of pharmacy trips and decreases the likelihood that one prescription lapses while others remain current. Many pharmacies, including online services like TabOrderRx, offer synchronization as a standard service.
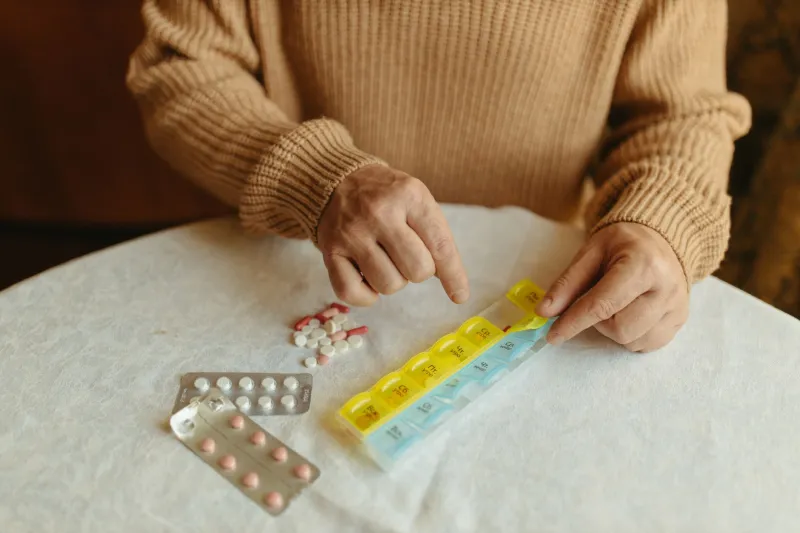
Use adherence technology deliberately. Pill organizers remain one of the most effective low-technology adherence tools available. For patients managing complex regimens, weekly organizers provide a visual record of missed doses that forgetfulness alone cannot. Smartphone applications such as Medisafe, MyTherapy, and CareZone offer reminder functions, refill tracking, and interaction alerts.
Have an honest conversation about side effects before they become a reason to quit. When beginning a new medication, ask your prescriber specifically: What side effects should I expect in the first two weeks? Which ones warrant a call to your office? Which ones are likely to resolve on their own? Setting expectations in advance dramatically reduces the likelihood that a patient will discontinue without guidance.
Establish a measurable outcome. Work with your prescriber to identify a specific, trackable marker of treatment success—a target blood pressure reading, a goal A1C, a mood rating scale. Having a number to work toward transforms adherence from an abstract obligation into a goal-directed behavior.
Address cost proactively. If the cost of a medication is a barrier, say so. Prescribers can often substitute a therapeutically equivalent generic, identify manufacturer assistance programs, or adjust quantities to reduce out-of-pocket expense. Pharmacists can check multiple pricing sources and apply discount programs. Silence about cost is one of the most expensive decisions a patient can make.
The Role of the Pharmacist in Adherence
Pharmacists are uniquely positioned in the healthcare system to identify and address adherence problems. Unlike physicians, who may see a patient once or twice a year, pharmacists interact with many patients monthly. A pharmacist who notices that a refill is consistently requested late—or not at all—has an opportunity to initiate a conversation that a physician may never have.
Medication therapy management programs, available through many insurance plans and pharmacy services, provide structured one-on-one consultations specifically designed to review regimens, identify barriers to adherence, and develop personalized solutions. These sessions are frequently underutilized because patients are unaware they exist.
A Different Way to Think About Adherence
The language of medication adherence carries an implicit judgment: the patient is expected to comply with a prescribed regimen, and failure to do so is a form of non-compliance. This framing places the entire burden of success on the patient and ignores the many systemic, financial, and psychological factors that shape medication-taking behavior.
A more productive framework treats adherence as a shared responsibility between the patient, the prescriber, the pharmacist, and the healthcare system. Prescriptions that are too expensive, too complex, too poorly explained, or too poorly monitored will be abandoned—regardless of the patient's intentions.
If you have stopped taking a medication, or are struggling to maintain a regimen, the most important step is to say so—to your physician, your pharmacist, or both. The conversation may be uncomfortable, but it is far less costly than the alternative.


